Schizophrenia and psychosis — Schizophrenia is a condition involving disturbances in perception, thinking and functioning, with considerable variation between people and over time. Psychosis is a symptom-related concept that can occur in several conditions; it is not synonymous with schizophrenia. Schizophrenia does not mean a split personality, and a diagnosis does not imply that someone is violent.
Positive and negative symptoms — Positive symptoms involve experiences or behaviours added to ordinary functioning; negative symptoms involve reduction or loss of functions. Positive does not mean desirable and negative does not mean morally bad. The categories describe features rather than two mutually exclusive kinds of person, and their severity can change.
Hallucinations and delusions — A hallucination is a perception-like experience without a corresponding external stimulus, such as hearing a voice when no speaker is present. A delusion is a firmly held belief inconsistent with evidence and the person's cultural context. One concerns experience and the other belief; diagnosis requires contextual professional assessment rather than labelling any unusual claim.
Speech poverty and avolition — Speech poverty, or alogia, involves reduced quantity or elaboration of speech. Avolition is reduced motivation to initiate and sustain goal-directed activity. Distinguish these from choosing silence, ordinary tiredness or laziness. Medication effects, depression and environmental opportunity can also affect observed behaviour and must be considered.
Co-morbidity — Co-morbidity means two or more conditions occur in the same person, such as schizophrenia alongside depression. It can complicate assessment, outcome measurement and treatment planning. It does not by itself prove that either diagnosis is invalid; investigate whether the criteria distinguish processes and whether the combination changes prognosis or support needs.
Symptom overlap — Features such as low motivation or hallucinations can occur in more than one condition. Overlap challenges an inference from one symptom to one diagnosis. Consider the pattern, timing, context and possible alternative explanations; a quiz vignette identifies a concept and is not enough evidence to diagnose a real person.
Culture and gender bias — Diagnostic judgments can be influenced by assumptions about culturally meaningful beliefs, language, emotional expression or gendered behaviour. A higher recorded diagnosis rate may reflect exposure to adversity, access to care, referral, measurement bias or several factors together. Do not treat every rate difference as proof of biology or, conversely, as proof that all cases were misdiagnosed.
Assessing diagnostic evidence — Compare how information was obtained, who was represented and whether the same features were interpreted consistently across settings. Translation and culturally informed interviewing can improve interpretation. A research classification and a complete clinical assessment have different purposes; transparent limitations are preferable to a stereotype presented as an objective test.
Genetic and neural explanations
Genetic vulnerability — Family, twin and adoption designs investigate inherited contributions to vulnerability. Increased resemblance among closer biological relatives is consistent with genetic influence, but relatives may also share environments. The condition is polygenic: many variants can contribute small effects rather than one gene inevitably producing the same outcome.
Twin comparisons — Higher concordance among monozygotic (identical) than dizygotic (non-identical) twins can support a genetic contribution, subject to comparable environmental similarity and ascertainment, meaning how cases are identified and recruited. Concordance below 100 percent among monozygotic twins is inconsistent with a simple fully penetrant genetic account in which having the relevant genetic variant always produces the condition. It does not demonstrate that genes are irrelevant or quantify the cause of a particular person's experiences.
Adoption and methodological limits — Adoption comparisons can partly separate biological relatedness from rearing, but prenatal conditions, selective placement and continued family contact complicate interpretation. Diagnoses and historical institutional practices can differ across cohorts. Use converging designs instead of treating one pedigree or adoption result as a controlled experiment on genes.
Neural correlates — A neural correlate is a measured association between a neural characteristic and a symptom or diagnosis. Functional differences in networks involved in auditory processing, monitoring or motivation may be relevant, but medication, symptoms, stress and plasticity can affect brain measurements. An image is not direct proof that the observed feature caused the condition.
Dopamine accounts — Early accounts emphasised excessive dopamine activity; later accounts distinguish pathways and functions, including altered presynaptic dopamine functioning associated with psychotic symptoms and possible lower activity in some cortical processes. Avoid saying dopamine is uniformly too high everywhere or that all symptoms have one chemical explanation. Other neurotransmitters and circuits are investigated too.
Evidence from drugs and imaging — Dopamine-related drugs and receptor-blocking treatments can inform mechanisms, while imaging can compare activity or receptor-related measures. A treatment's effect does not prove the untreated condition originated as a simple chemical imbalance: reducing pain with an analgesic does not establish analgesic deficiency. Examine time course, symptom specificity and alternative explanations.
Evaluating biological explanations — Biological findings can support testable mechanisms and treatment development while remaining incomplete. Heterogeneous symptom profiles, small samples, prior medication and correlational designs complicate interpretation. Explanations should accommodate environmental risk, development and individual variation rather than equating an association with genetic destiny.
Family and cognitive explanations
Historical family hypotheses — Historical accounts proposed that confusing relationships or communication contributed to schizophrenia. The discredited schizophrenogenic-mother idea blamed a cold or controlling mother; it lacks adequate supporting evidence and should not be presented as an established cause. Families can be important sources of support, and relatives' behaviour may itself be affected by living with illness and adversity.
Double-bind theory — The double-bind hypothesis proposed repeated incompatible messages in an important relationship with no safe way to challenge or leave the contradiction. It offers a communication-based mechanism but is difficult to operationalise and test prospectively. Retrospective examples do not establish that such communication caused schizophrenia, and ordinary contradictory messages are not sufficient evidence.
Expressed emotion — Expressed emotion describes aspects of relatives' responses, particularly criticism, hostility and emotional over-involvement. High expressed emotion has been associated with relapse risk in some studies. That association concerns the course of an existing condition and can be reciprocal; it does not establish that relatives caused its original onset.
Family evidence and confounds — Illness severity may influence both family stress and later relapse, creating a third-variable explanation. Prospective measurement, independent coding and comparison of interventions help test mechanisms. Assess cultural meaning and practical pressures; avoid assigning blame from a correlational family measure.
Metarepresentation and monitoring — Cognitive accounts propose difficulties representing one's own and others' mental states or recognising thoughts and actions as self-generated. Misattributing inner speech as an external voice is a proposed mechanism for some hallucinations. It is a hypothesis about particular experiences, not evidence that a person has no insight into anything.
Central control and thought processing — Difficulties inhibiting automatic responses or selecting relevant information may contribute to disorganised thought and speech. Tasks such as interference tests can examine control processes, but task impairment is not unique to schizophrenia. A cognitive model must connect measured processing differences to particular symptoms rather than describe poor performance alone.
Evaluating cognitive explanations — Cognitive accounts connect mechanisms with experiences and may inform psychological support. However, an observed processing difficulty could be a cause, consequence or correlate, and explaining maintenance does not necessarily explain onset. Biological and cognitive levels can describe different parts of the same process rather than competing exclusive causes.
Medication and treatment evaluation
Typical antipsychotics — Typical antipsychotics such as chlorpromazine act substantially through dopamine D2 receptor antagonism, meaning that they block dopamine's action at these receptors, and can reduce positive symptoms. They do not erase every symptom or demonstrate a universal dopamine excess. Potential adverse effects include movement-related difficulties and sedation; prescribing decisions require individual clinical assessment rather than a school revision rule.
Atypical antipsychotics — Atypical antipsychotics, including clozapine and risperidone, have differing receptor profiles and risk-benefit patterns. Many act on dopamine and serotonin systems; they are not one identical mechanism and are not free of movement or metabolic adverse effects, such as weight gain or changes in blood glucose and cholesterol. Clozapine can be used for treatment-resistant illness and requires particular monitoring because of potentially serious adverse effects.
Effectiveness and appropriateness — Evaluate reductions in symptoms, relapse, daily functioning and quality of life alongside adverse effects, acceptability and treatment engagement. A short-term change on one scale does not establish long-term recovery. Compare baseline severity, allocation, blinding, attrition and follow-up; distinguish statistical significance from a meaningful change for participants.
Interpreting medication comparisons — Randomised comparisons can improve causal inference but placebo and active-comparator trials answer different questions. Side effects can reveal treatment allocation, and differential withdrawal may bias outcomes. Sponsorship, publication bias and selective reporting require scrutiny; use systematic evidence rather than claiming that one favourable trial settles every treatment choice.
CBT and family therapy
CBT for psychosis — CBT is a collaborative approach exploring the meaning of experiences and developing ways to reduce distress and improve coping. For example, therapist and client can examine evidence for an interpretation and consider alternatives without humiliating confrontation. Reducing conviction or distress is different from guaranteeing that voices disappear or proving every experience was caused by irrational thought.
CBT mechanisms and limits — Formulation links experiences, beliefs, emotion and behaviour in the person's context. Coping strategies and carefully agreed behavioural tests can challenge unhelpful interpretations. Engagement, therapist skill and access matter; comparison with supportive contact helps determine whether change reflects specific techniques, therapeutic alliance or both.
Family therapy processes — Family interventions can include education about experiences and treatment, communication skills, problem solving, stress management and relapse planning. They aim to strengthen support and reduce distress, not expose a supposedly guilty parent. Include the person and relatives appropriately, with consent and attention to confidentiality and varied family arrangements.
Evaluating psychological treatments — Compare relapse, hospitalisation, distress and functioning over suitable follow-up, not only immediate self-report. Randomisation, independent outcome assessment, treatment fidelity and attrition affect conclusions. Therapy can require time and trained staff, and people differ in access and preferences; the same intervention need not benefit everyone equally.
Interactionism and the diathesis-stress model
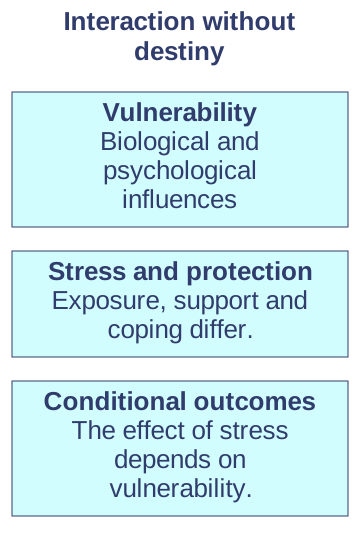
Vulnerability and stress — A diathesis is a vulnerability; stress is an experience or condition that may contribute to onset or relapse. Vulnerability can involve biological and psychological influences, and stress can include social adversity as well as acute events. The model proposes interaction: the effect of stress depends partly on vulnerability rather than one universal threshold applying to everyone.The model proposes conditional effects and protective influences, not one inevitable threshold or a claim that relatives caused the condition.
From simple to developed models — A simple inherited-vulnerability model is useful for introducing interaction but can be too narrow. Developmental experiences may affect later vulnerability and stress regulation, while protective support changes exposure or coping. Genetic influence does not mean inevitability, and not every person exposed to an adversity develops the same condition.
Integrated explanation and treatment — An interactionist formulation can justify combined biological, psychological and social support addressing different processes. Improvement with a combined programme does not isolate which element helped unless the comparison is designed to test components. Compare medication alone, psychological support alone where appropriate and combined care using ethical, clinically suitable designs.
Making a reasoned judgment — Evaluate whether evidence predicts onset, relapse, distress or functioning, since these are different outcomes. Link each explanation to a mechanism, relevant research and causal limitations; link each therapy to both effectiveness and appropriateness. A diagnosis label is not a complete explanation, and a short knowledge quiz cannot certify clinical judgment or extended evaluative writing.
Test yourself
50 questions · Random sets of 10. These quick checks support revision; practise longer explanations and justified judgements too.
 Mr Kidman's Classroom